Omphalocele (Exomphalos)
Abdominal organs outside the tummy at the navel, in a covering sac.
What is Omphalocele (Exomphalos)?
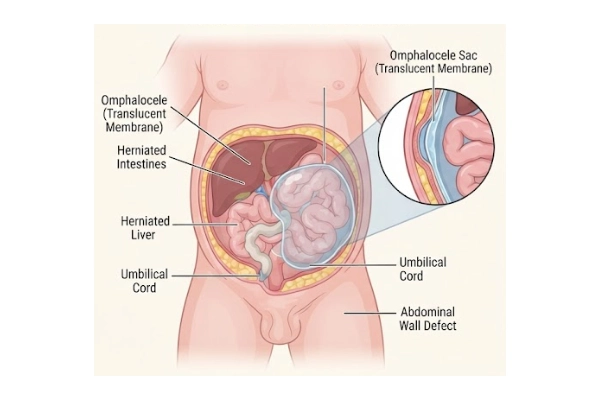
In an omphalocele, part of the abdominal contents — bowel, and sometimes the liver — lies outside the abdomen at the base of the umbilical cord, covered by a thin membrane sac.
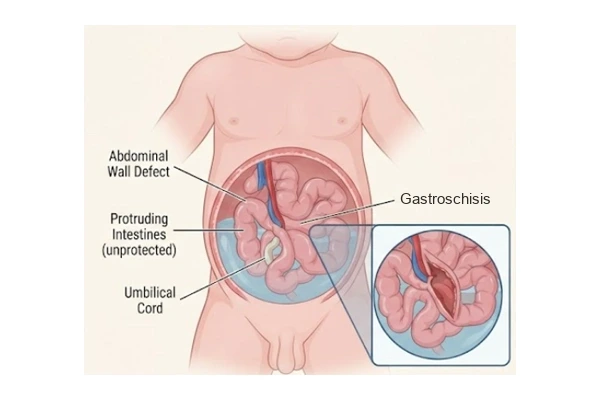
The covering sac is the important difference from gastroschisis, where the bowel is exposed with no covering at all.
It is usually seen on an antenatal scan. That advance warning is valuable, because it allows delivery to be planned where paediatric surgery and newborn intensive care are available.
Omphalocele is frequently associated with other conditions, particularly of the heart and chromosomes, so a baby is assessed thoroughly rather than treated as an isolated abdominal wall problem.
The outlook depends more on the associated conditions and the size of the defect than on the abdominal wall itself.
In your language
Omphalocele (Exomphalos)
Abdominal organs outside the tummy at the navel, in a covering sac.
In an omphalocele, part of the abdominal contents — bowel, and sometimes the liver — lies outside the abdomen at the base of the umbilical cord, covered by a thin membrane sac.
ஓம்பலோசீல் (தொப்புள் வழி குடல் வெளியேற்றம்)
ஓம்பலோசீல் என்பது பிறக்கும்போது குழந்தையின் குடல் (சில சமயம் கல்லீரலும்) தொப்புள் பகுதியில் ஒரு மெல்லிய சவ்வுப் பையினுள் வெளியே இருக்கும் நிலை. இந்த மூடும் சவ்வுதான் காஸ்ட்ரோஸ்கிசிஸ் நிலையிலிருந்து இதை வேறுபடுத்துகிறது. பொதுவாக கர்ப்ப கால ஸ்கேனில் தெரியும் — அப்படித் தெரிந்தால், குழந்தை மருத்துவ அறுவை சிகிச்சை மற்றும் NICU வசதி உள்ள இடத்தில் பிரசவத்தைத் திட்டமிடுங்கள். பிறந்த உடன்: பையை மூடி, சுத்தமாகவும் ஈரப்பதத்துடனும் வைத்து, குழந்தையை சூடாக வைத்து உடனடியாக மருத்துவமனைக்கு கொண்டு செல்லுங்கள். உள்ளே தள்ள முயற்சிக்க வேண்டாம். இதயம் உள்ளிட்ட பிற குறைபாடுகளும் இருக்கலாம் என்பதால் முழு பரிசோதனை அவசியம்.
ഓംഫലോസീൽ
ജനിക്കുമ്പോൾ കുഞ്ഞിന്റെ കുടൽ (ചിലപ്പോൾ കരളും) പൊക്കിൾ ഭാഗത്ത് നേർത്ത ഒരു സഞ്ചിക്കുള്ളിൽ പുറത്തായിരിക്കുന്ന അവസ്ഥയാണ് ഓംഫലോസീൽ. ഈ ആവരണമാണ് ഗ്യാസ്ട്രോസ്കിസിസിൽ നിന്ന് ഇതിനെ വ്യത്യസ്തമാക്കുന്നത്. സാധാരണ ഗർഭകാല സ്കാനിൽ കാണാം — അങ്ങനെയെങ്കിൽ പീഡിയാട്രിക് സർജറിയും NICU-വും ഉള്ളിടത്ത് പ്രസവം ആസൂത്രണം ചെയ്യുക. ജനിച്ചയുടൻ: സഞ്ചി മൂടി, ഈർപ്പത്തോടെ സൂക്ഷിച്ച്, കുഞ്ഞിനെ ചൂടോടെ ഉടൻ ആശുപത്രിയിൽ എത്തിക്കുക. ഉള്ളിലേക്ക് തള്ളാൻ ശ്രമിക്കരുത്.
What Parents Notice
Not every child shows every sign. If something on this list matches your child, it is worth an examination rather than a guess.
- A visible sac at the base of the umbilical cord containing bowel, and in larger defects the liver
- Seen at birth, or diagnosed on an antenatal ultrasound
- Breathing difficulty where the chest and abdomen are small relative to the contents
- Feeding difficulty
- Features of associated conditions — heart abnormalities, an enlarged tongue, low blood sugar, or other syndromic features
- A ruptured sac at birth, which is an emergency
How It Is Confirmed
- Antenatal ultrasound, usually in the second trimester
- Examination at birth — the diagnosis is visible
- Echocardiogram, because associated heart abnormalities are common and matter for anaesthesia
- Ultrasound of the kidneys and abdomen
- Blood glucose monitoring, particularly where Beckwith-Wiedemann syndrome is suspected
- Chromosomal and genetic assessment where indicated
How It Is Treated
- Immediate care at birth: keep the sac covered, warm and moist, protect it from injury, place a nasogastric tube, start intravenous fluids and keep the baby warm.
- Do not attempt to push the contents back — the sac must be protected until the baby is assessed.
- A small omphalocele is usually closed in a single operation soon after birth.
- A large or giant omphalocele is often managed in stages: the contents are gradually reduced over days to weeks using a silo or by allowing the sac to epithelialise, with closure of the abdominal wall done later.
- NICU care, ventilation where needed, and intravenous nutrition until feeds are established.
- Associated heart and other conditions are treated alongside, and where the baby needs care beyond what is available on the day, referral is arranged promptly and clearly.
Does My Child Need Surgery?
Not every child with Omphalocele (Exomphalos) needs an operation. These are the situations in which surgery is advised — and the decision is always made after examining your child, never from a description alone.
Early primary closure for small defects, once the baby is stable
Emergency intervention if the sac has ruptured
Staged closure over days to weeks for large or giant omphaloceles, with the timing guided by the baby’s breathing and the abdominal capacity
Delayed closure after months of conservative management in selected giant defects, which is a recognised and safe approach
What Happens Over Time
Determined more by the associated conditions — particularly of the heart and chromosomes — than by the abdominal wall itself. Babies with a small defect and no other significant abnormality generally do very well. Giant omphaloceles need a longer, staged course and often prolonged breathing support.
This describes what usually happens, not what will happen to your child. The surgeon will give you a specific picture after examining them.
Can It Be Prevented?
It cannot be prevented. Detection on an antenatal scan allows delivery to be planned where the right care is available, which does change what happens on day one.
From First Visit to Going Home
What happens, in order, so that nothing on the day comes as a surprise.
Consultation
Dr. Pratheep Samraj examines your child and goes through the history, earlier reports and any treatment already given.
Investigation
Only the tests that change the decision are asked for — commonly an ultrasound, blood tests, and occasionally an X-ray or a scopy.
Explanation
You are told what the condition is, whether it needs surgery, what happens if you wait, and what the operation involves.
Treatment
If surgery is appropriate it is planned with paediatric anaesthetic cover, with ICU and NICU support available in the hospital.
Follow-up
You go home with written instructions and a review date, and you can reach the hospital by phone or WhatsApp in between.
Hospital stay
Weeks, and considerably longer for a giant omphalocele or where associated conditions need treatment.
Recovery at home
Feeding is established gradually. Breathing support is often needed early on where the abdominal cavity is small.
Follow-up
Long-term — growth, feeding, the abdominal wall repair, and monitoring of any associated conditions.
Please bring with you: all previous scan reports, blood test reports, discharge summaries, records of any earlier operation, current medicines, and your child’s immunisation card. Photographs on your phone of a swelling that comes and goes are genuinely useful.
Please note: this page is general information about Omphalocele (Exomphalos), not advice about your child. Timing, suitability for surgery and the expected result differ from child to child and are decided only after clinical evaluation.
Questions Parents Ask
If your question is not here, send it on WhatsApp — you will get an answer from the hospital team.
Dr. Pratheep Samraj
Consultant Paediatric & Neonatal Surgeon · Palliyadi, Kanyakumari
Super-specialist surgical care for newborns, infants and children, with expertise in paediatric urology, congenital anomalies, gastro-intestinal surgery and minimally invasive surgery.
Related Conditions
Keep the sac covered and warm, and get the baby to a surgeon.
Do not try to push the contents back in — the sac must be protected until the baby is assessed. This is usually seen before birth, so if your scan has shown it, talk to us before the delivery.
Consultation 10:00 AM - 1:00 PM & 4:00 PM - 8:00 PM · 24-hour laboratory & pharmacy
In an emergency — green vomiting in a baby, a groin swelling that will not go back, severe tummy pain, or a newborn not passing urine or meconium — come straight to the hospital or to your nearest emergency department. Do not wait for a reply to a message.