Pyloric Stenosis
Forceful projectile vomiting in a baby of a few weeks old.
What is Pyloric Stenosis?
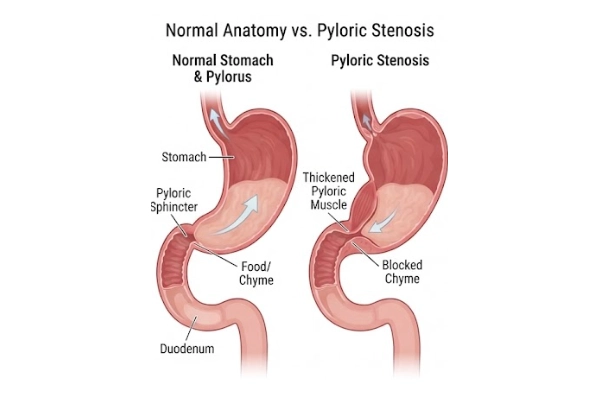
The pylorus is the muscular outlet at the bottom of the stomach. In pyloric stenosis this muscle thickens over the first weeks of life until milk can no longer pass through into the intestine.
The baby is typically born healthy, feeds well for the first two or three weeks, and then starts vomiting — forcefully, right after feeds, and increasingly.
The vomit is milk, never green. It shoots out rather than dribbling. And crucially the baby is hungry immediately afterwards and wants to feed again.
It is more common in boys, especially first-born boys, and sometimes runs in families. Typical age at presentation is 3 to 6 weeks.
This is not a surgical emergency in the first minutes, but it is urgent: the losses from repeated vomiting upset the baby’s salts and hydration, and those must be corrected before any anaesthetic.
In your language
Pyloric Stenosis
Forceful projectile vomiting in a baby of a few weeks old.
The pylorus is the muscular outlet at the bottom of the stomach. In pyloric stenosis this muscle thickens over the first weeks of life until milk can no longer pass through into the intestine.
இரைப்பை வெளியேற்ற வாய் அடைப்பு (பைலோரிக் ஸ்டெனோசிஸ்)
பிறந்து 3–6 வாரங்களில் குழந்தை பால் குடித்த உடனேயே பீய்ச்சி அடித்தாற்போல வாந்தி எடுத்தால் இது பைலோரிக் ஸ்டெனோசிஸ் ஆக இருக்கலாம். வாந்தி பச்சை நிறத்தில் இருக்காது; வாந்தி எடுத்த உடனேயே குழந்தைக்கு மீண்டும் பசிக்கும். எடை குறையும், சிறுநீர் குறையும். ஸ்கேன் மூலம் உறுதி செய்யப்படும். முதலில் நரம்பு வழி திரவம் கொடுத்து உடல் நீர்ச்சத்தையும் உப்புச் சத்தையும் சரிசெய்ய வேண்டும் — பின்னரே அறுவை சிகிச்சை. அறுவை சிகிச்சை (பைலோரோமையோட்டமி) எளிமையானது; சில மணி நேரங்களில் பால் தொடங்கிவிடலாம்.
പൈലോറിക് സ്റ്റെനോസിസ്
ജനിച്ച് 3–6 ആഴ്ചയ്ക്കുള്ളിൽ കുഞ്ഞ് പാൽ കുടിച്ച ഉടനെ ശക്തിയായി ചീറ്റി ഛർദ്ദിക്കുന്നുവെങ്കിൽ അത് പൈലോറിക് സ്റ്റെനോസിസ് ആകാം. ഛർദ്ദിയിൽ പച്ച നിറം ഉണ്ടാകില്ല; ഛർദ്ദിച്ച ഉടനെ കുഞ്ഞിന് വീണ്ടും വിശക്കും. തൂക്കം കുറയും, മൂത്രം കുറയും. സ്കാനിലൂടെ സ്ഥിരീകരിക്കും. ആദ്യം ഞരമ്പിലൂടെ ദ്രാവകം നൽകി നിർജ്ജലീകരണവും ലവണങ്ങളും ശരിയാക്കണം — അതിനുശേഷമേ ശസ്ത്രക്രിയ ചെയ്യൂ. ശസ്ത്രക്രിയയ്ക്കു ശേഷം മണിക്കൂറുകൾക്കുള്ളിൽ പാൽ തുടങ്ങാം.
What Parents Notice
Not every child shows every sign. If something on this list matches your child, it is worth an examination rather than a guess.
- Forceful projectile vomiting immediately after feeds, becoming more frequent and more forceful
- The vomit is milk without any green colour
- The baby is hungry again straight after vomiting
- Poor weight gain, or weight loss
- Fewer wet nappies and fewer stools
- Dehydration — a sunken fontanelle, dry mouth, sunken eyes, lethargy
- Visible waves moving across the upper tummy during a feed
- A firm olive-shaped lump felt in the upper abdomen by an experienced examiner
How It Is Confirmed
- Ultrasound of the abdomen — the confirming test, measuring the thickness and length of the pyloric muscle
- Blood tests for electrolytes and acid-base status, which characteristically show low chloride and low potassium with alkalosis
- Clinical examination, including a test feed to observe the stomach waves and feel for the pyloric mass
How It Is Treated
- The first priority is not surgery but resuscitation — intravenous fluids to correct dehydration and the electrolyte disturbance. This usually takes 24 to 48 hours and is not a delay, it is the treatment that makes anaesthesia safe.
- A tube is placed to keep the stomach empty and feeds are stopped.
- The operation is a pyloromyotomy: the thickened muscle is divided along its length, leaving the inner lining intact, so the outlet opens up.
- It can be performed through a small incision or laparoscopically.
- Feeding restarts within hours after surgery and is built up over a day or so. Some vomiting in the first day afterwards is expected and settles.
Does My Child Need Surgery?
Not every child with Pyloric Stenosis needs an operation. These are the situations in which surgery is advised — and the decision is always made after examining your child, never from a description alone.
Once the diagnosis is confirmed and the baby’s fluids and electrolytes have been corrected — surgery is always the treatment for pyloric stenosis
It is never appropriate to operate on a dehydrated baby with abnormal electrolytes, however keen the family is to proceed
Medical treatment is not a substitute for the operation in standard practice
What Happens Over Time
Excellent. Once the muscle is divided the problem is solved permanently, babies feed and gain weight quickly, and there are no long-term consequences.
This describes what usually happens, not what will happen to your child. The surgeon will give you a specific picture after examining them.
Can It Be Prevented?
It cannot be prevented. It is more common in boys, particularly first-born boys, and sometimes runs in families.
From First Visit to Going Home
What happens, in order, so that nothing on the day comes as a surprise.
Consultation
Dr. Pratheep Samraj examines your child and goes through the history, earlier reports and any treatment already given.
Investigation
Only the tests that change the decision are asked for — commonly an ultrasound, blood tests, and occasionally an X-ray or a scopy.
Explanation
You are told what the condition is, whether it needs surgery, what happens if you wait, and what the operation involves.
Treatment
If surgery is appropriate it is planned with paediatric anaesthetic cover, with ICU and NICU support available in the hospital.
Follow-up
You go home with written instructions and a review date, and you can reach the hospital by phone or WhatsApp in between.
Hospital stay
Usually 3 to 5 days in total, including the period of correction before surgery.
Recovery at home
Feeds are re-established within 24 to 48 hours. Once feeding, babies typically gain weight rapidly and catch up.
Follow-up
One review after discharge. There are no long-term problems expected after a pyloromyotomy.
Please bring with you: all previous scan reports, blood test reports, discharge summaries, records of any earlier operation, current medicines, and your child’s immunisation card. Photographs on your phone of a swelling that comes and goes are genuinely useful.
Please note: this page is general information about Pyloric Stenosis, not advice about your child. Timing, suitability for surgery and the expected result differ from child to child and are decided only after clinical evaluation.
Questions Parents Ask
If your question is not here, send it on WhatsApp — you will get an answer from the hospital team.
Dr. Pratheep Samraj
Consultant Paediatric & Neonatal Surgeon · Palliyadi, Kanyakumari
Super-specialist surgical care for newborns, infants and children, with expertise in paediatric urology, congenital anomalies, gastro-intestinal surgery and minimally invasive surgery.
Related Conditions
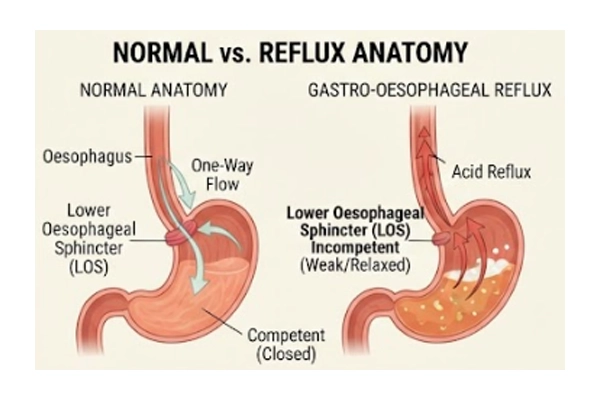
Projectile vomiting in a baby of a few weeks has a cause worth finding.
It is not reflux and it is not the feed — an ultrasound settles it in minutes. The operation that follows is small, but the baby must be rehydrated first.
Consultation 10:00 AM - 1:00 PM & 4:00 PM - 8:00 PM · 24-hour laboratory & pharmacy
In an emergency — green vomiting in a baby, a groin swelling that will not go back, severe tummy pain, or a newborn not passing urine or meconium — come straight to the hospital or to your nearest emergency department. Do not wait for a reply to a message.