Posterior Urethral Valves
A blockage in the urinary passage in newborn boys.
What is Posterior Urethral Valves?
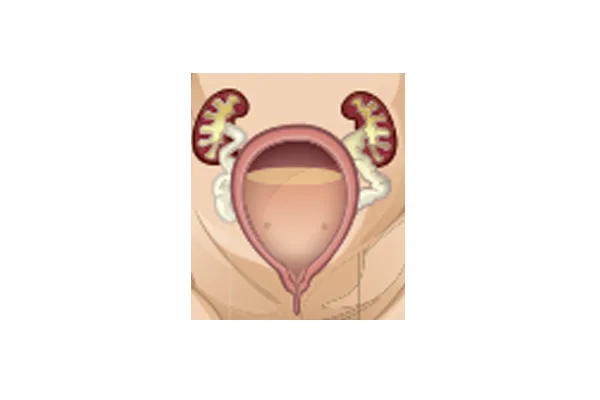
Posterior urethral valves are thin folds of tissue inside the urinary passage of a boy, present from birth, which act like a one-way flap and obstruct the outflow of urine.
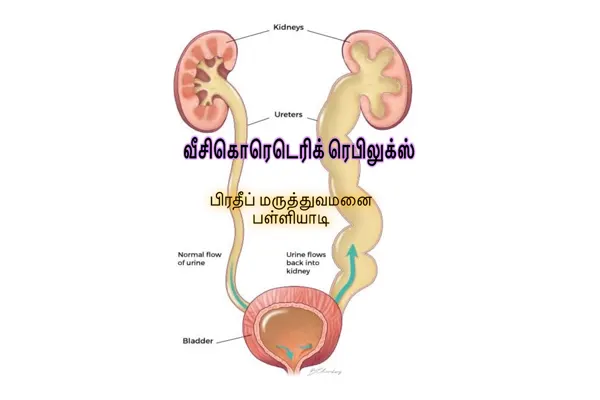
It occurs only in boys. Because the obstruction is present before birth, the whole urinary system above it is affected: the bladder wall thickens and works against pressure, the ureters dilate, and the kidneys can be damaged in the womb.
This is the most important obstructive urinary condition in newborn boys, and it is one where speed genuinely matters. It is treatable, and early treatment protects what kidney function the baby has.
Even after the valves are removed, the bladder often remains thick-walled and poorly compliant. Long-term management of the bladder is as important as removing the valves.
In your language
Posterior Urethral Valves
A blockage in the urinary passage in newborn boys.
Posterior urethral valves are thin folds of tissue inside the urinary passage of a boy, present from birth, which act like a one-way flap and obstruct the outflow of urine.
சிறுநீர்க்குழாய் வால்வு அடைப்பு (PUV)
PUV என்பது ஆண் குழந்தைகளில் மட்டும் ஏற்படும், சிறுநீர்க்குழாயில் உள்ள பிறவி அடைப்பு. புதிதாகப் பிறந்த ஆண் குழந்தை சிறுநீரை சீராக ஒரு நீரோட்டமாக கழிக்க வேண்டும். சொட்டு சொட்டாக வருதல், முக்கி முக்கி கழித்தல், அடிவயிற்றில் வீக்கம் இருந்தால் உடனடியாக மருத்துவரைப் பாருங்கள். MCUG பரிசோதனை மூலம் உறுதி செய்யப்படும். சிஸ்டோஸ்கோப் மூலம் வால்வை நீக்கும் சிகிச்சை — வெளிப்புற வெட்டு தேவையில்லை. இது சிறுநீரகத்தைப் பாதுகாக்க அவசரமாகச் செய்ய வேண்டிய சிகிச்சை. பின்னர் நீண்ட கால கண்காணிப்பு கட்டாயம்.
മൂത്രനാളിയിലെ വാൽവ് തടസ്സം (PUV)
ആൺകുഞ്ഞുങ്ങളിൽ മാത്രം കാണുന്ന, മൂത്രനാളിയിലെ ജന്മനായുള്ള തടസ്സമാണ് PUV. നവജാത ആൺകുഞ്ഞ് മൂത്രം ധാരയായി ഒഴിക്കണം. തുള്ളിത്തുള്ളിയായി വരിക, ബലം പിടിക്കുക, അടിവയറ്റിൽ വീക്കം എന്നിവയുണ്ടെങ്കിൽ ഉടൻ ഡോക്ടറെ കാണണം. MCUG പരിശോധനയിലൂടെ സ്ഥിരീകരിക്കും. സിസ്റ്റോസ്കോപ്പിലൂടെ വാൽവ് നീക്കുന്ന ചികിത്സയാണ് — പുറത്ത് മുറിവ് വേണ്ട. വൃക്ക സംരക്ഷിക്കാൻ ഇത് അടിയന്തരമായി ചെയ്യേണ്ടതാണ്. പിന്നീട് ദീർഘകാല നിരീക്ഷണം നിർബന്ധമാണ്.
What Parents Notice
Not every child shows every sign. If something on this list matches your child, it is worth an examination rather than a guess.
- A poor, dribbling or interrupted urinary stream in a newborn boy — a baby boy should pass urine as a stream, not a dribble
- Straining to pass urine
- A distended bladder felt as a swelling in the lower tummy
- Poor feeding, vomiting, lethargy or failure to gain weight
- Urinary tract infection with fever in a young infant
- Antenatal scan showing swollen kidneys on both sides, a thick-walled bladder and reduced amniotic fluid
- In older boys not diagnosed as babies: daytime wetting, straining, and repeated infections
How It Is Confirmed
- Ultrasound of the kidneys, ureters and bladder
- MCUG — the definitive test, which shows the dilated posterior urethra and the thick-walled bladder
- Blood tests for creatinine and electrolytes, repeated over the first days — the level after a few days reflects the baby’s own kidney function rather than the mother’s
- Cystoscopy, which both confirms the valves and allows them to be treated in the same sitting
- DMSA scan later to assess kidney scarring and split function
How It Is Treated
- First, the bladder is drained with a catheter and the baby is stabilised — fluids, electrolytes and infection are corrected before anything else.
- The definitive treatment is endoscopic valve ablation: a fine cystoscope is passed through the urinary passage and the valve leaflets are divided. There is no external cut.
- A very small or unstable baby may need a temporary vesicostomy — a small opening that lets the bladder drain to the skin — until definitive treatment is safe.
- Afterwards, treatment focuses on the bladder and kidneys: medications for bladder pressure, timed voiding, treating constipation, preventing infection, and monitoring growth and blood pressure.
- A minority of boys develop chronic kidney disease over years and need nephrology care. This is why follow-up does not stop after the valves are removed.
Does My Child Need Surgery?
Not every child with Posterior Urethral Valves needs an operation. These are the situations in which surgery is advised — and the decision is always made after examining your child, never from a description alone.
Once the diagnosis is confirmed, valve ablation is done as soon as the baby is stable — this is not a condition to observe
A catheter is placed immediately at presentation to relieve the obstruction while tests are completed
Urgent treatment is needed if the baby has infection, rising creatinine or an over-distended bladder
An older boy diagnosed late still needs the valves treated, along with full bladder and kidney assessment
What Happens Over Time
This is the one paediatric urology condition where outlook depends heavily on damage done before birth. Many boys do well after the valves are removed. A minority develop reduced kidney function during childhood or adolescence, and a small number eventually need dialysis or a transplant. Lifelong follow-up is how problems are caught while they can still be managed.
This describes what usually happens, not what will happen to your child. The surgeon will give you a specific picture after examining them.
Can It Be Prevented?
It cannot be prevented. Early diagnosis and prompt relief of the obstruction are what protect kidney function.
From First Visit to Going Home
What happens, in order, so that nothing on the day comes as a surprise.
Consultation
Dr. Pratheep Samraj examines your child and goes through the history, earlier reports and any treatment already given.
Investigation
Only the tests that change the decision are asked for — commonly an ultrasound, blood tests, and occasionally an X-ray or a scopy.
Explanation
You are told what the condition is, whether it needs surgery, what happens if you wait, and what the operation involves.
Treatment
If surgery is appropriate it is planned with paediatric anaesthetic cover, with ICU and NICU support available in the hospital.
Follow-up
You go home with written instructions and a review date, and you can reach the hospital by phone or WhatsApp in between.
Hospital stay
Newborns are usually admitted for several days, with NICU support where needed. The endoscopic procedure itself is short.
Recovery at home
The urinary stream should improve after ablation. Some babies pass large volumes of dilute urine for a period afterwards and need careful fluid and electrolyte management.
Follow-up
Lifelong. Regular ultrasound, kidney function, blood pressure and bladder assessment through childhood and into adult life.
Please bring with you: all previous scan reports, blood test reports, discharge summaries, records of any earlier operation, current medicines, and your child’s immunisation card. Photographs on your phone of a swelling that comes and goes are genuinely useful.
Please note: this page is general information about Posterior Urethral Valves, not advice about your child. Timing, suitability for surgery and the expected result differ from child to child and are decided only after clinical evaluation.
Questions Parents Ask
If your question is not here, send it on WhatsApp — you will get an answer from the hospital team.
Dr. Pratheep Samraj
Consultant Paediatric & Neonatal Surgeon · Palliyadi, Kanyakumari
Super-specialist surgical care for newborns, infants and children, with expertise in paediatric urology, congenital anomalies, gastro-intestinal surgery and minimally invasive surgery.
Related Conditions


Valves in a newborn boy are urgent, and the kidneys are what is at stake.
The bladder is drained first, then the valves are divided through the urinary passage with no external cut. If your son strains to pass urine or has a poor stream, do not wait for a routine appointment.
Consultation 10:00 AM - 1:00 PM & 4:00 PM - 8:00 PM · 24-hour laboratory & pharmacy
In an emergency — green vomiting in a baby, a groin swelling that will not go back, severe tummy pain, or a newborn not passing urine or meconium — come straight to the hospital or to your nearest emergency department. Do not wait for a reply to a message.