Malrotation & Volvulus
Bowel that is not fixed properly and can twist — a true emergency.
What is Malrotation & Volvulus?
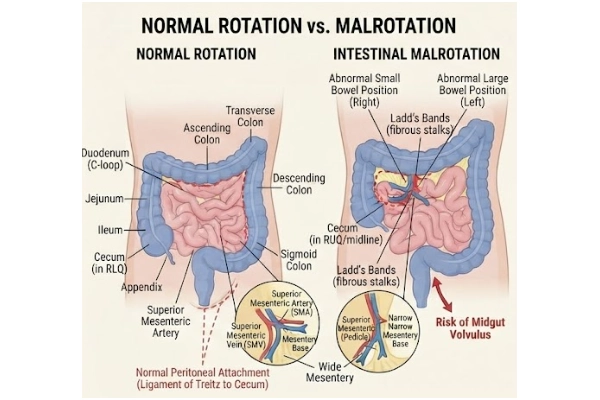
During development the bowel rotates and then becomes fixed to the back of the abdomen along a broad base. In malrotation this rotation is incomplete, so the bowel hangs from a narrow stalk instead.
A narrow stalk can twist. When it does — midgut volvulus — the blood supply to almost the entire small intestine is cut off.
This is the most time-critical condition in paediatric surgery. Bowel begins to die within hours. A baby treated early can make a complete recovery; a baby treated late can lose most of the small intestine.
That is why one rule is repeated to every parent: green vomiting in a baby is an emergency until proven otherwise. It does not wait until morning.
Malrotation can also cause intermittent symptoms in older children — recurrent bouts of tummy pain and vomiting from partial twisting or from bands compressing the bowel.
In your language
Malrotation & Volvulus
Bowel that is not fixed properly and can twist — a true emergency.
During development the bowel rotates and then becomes fixed to the back of the abdomen along a broad base. In malrotation this rotation is incomplete, so the bowel hangs from a narrow stalk instead.
குடல் திருகல் (மால்ரொடேஷன் & வால்வுலஸ்)
இது குழந்தை மருத்துவ அறுவை சிகிச்சையில் மிக அவசரமான நிலை. குடல் சரியாக நிலைநிறுத்தப்படாததால் திருகிக்கொள்ளும்; அப்போது சிறுகுடலுக்கான ரத்த ஓட்டம் நின்றுவிடும். மணிநேரங்களுக்குள் குடல் இறக்கத் தொடங்கும். மிக முக்கியமான விதி: குழந்தை பச்சை நிறத்தில் வாந்தி எடுத்தால் அது அவசர நிலை — காலை வரை காத்திருக்க வேண்டாம், உடனடியாக மருத்துவமனைக்கு வாருங்கள். எக்ஸ்-ரே சாதாரணமாக இருந்தாலும் இந்த நிலையை நிராகரிக்க முடியாது. உடனடி அறுவை சிகிச்சை (லாட்ஸ் செயல்முறை) மூலம் குடலைக் காப்பாற்ற முடியும்.
കുടൽ പിരിയൽ (മാൽറൊട്ടേഷൻ)
പീഡിയാട്രിക് സർജറിയിലെ ഏറ്റവും അടിയന്തരമായ അവസ്ഥയാണിത്. കുടൽ ശരിയായി ഉറയ്ക്കാത്തതിനാൽ പിരിഞ്ഞുപോകും; അപ്പോൾ ചെറുകുടലിലേക്കുള്ള രക്തയോട്ടം നിലയ്ക്കും. മണിക്കൂറുകൾക്കുള്ളിൽ കുടൽ നശിക്കാൻ തുടങ്ങും. പ്രധാന നിയമം: കുഞ്ഞ് പച്ച നിറത്തിൽ ഛർദ്ദിച്ചാൽ അത് അടിയന്തരാവസ്ഥയാണ് — നേരം വെളുക്കാൻ കാത്തുനിൽക്കരുത്, ഉടൻ ആശുപത്രിയിൽ എത്തിക്കുക. എക്സ്-റേ സാധാരണമായാലും ഈ അവസ്ഥ ഒഴിവാക്കാനാവില്ല. ഉടനടിയുള്ള ശസ്ത്രക്രിയയിലൂടെ കുടൽ രക്ഷിക്കാം.
What Parents Notice
Not every child shows every sign. If something on this list matches your child, it is worth an examination rather than a guess.
- Sudden green or bile-stained vomiting in a previously well baby — the cardinal sign
- A baby who becomes irritable, then quiet, pale and unwell
- Abdominal distension, though the tummy can look deceptively normal early on
- Blood in the stool — a late and ominous sign meaning bowel is already compromised
- Refusing feeds, lethargy, shock
- In older children: recurrent episodes of vomiting and tummy pain, poor weight gain, or feeding difficulty over months
How It Is Confirmed
- Upper gastro-intestinal contrast study — the definitive test, showing the abnormal position of the duodeno-jejunal junction
- Ultrasound with Doppler, which can show the abnormal relationship of the mesenteric vessels and the whirlpool sign of a volvulus
- X-ray of the abdomen — useful but can be normal, which is why a normal X-ray never excludes the diagnosis
- Blood tests including acid-base status, which reflect how compromised the bowel is
- In a baby who is clearly unwell with bile-stained vomiting, the decision to operate is not delayed for the sake of completing investigations
How It Is Treated
- Immediate resuscitation: nothing by mouth, a nasogastric tube, intravenous fluids, antibiotics and correction of acidosis.
- Emergency surgery for volvulus. The bowel is untwisted, its viability assessed, and a Ladd procedure performed — abnormal bands are divided, the small bowel is placed on the right and the colon on the left, and the appendix is removed.
- If a segment of bowel is dead it is removed. If viability is uncertain, a planned second look operation within 24 to 48 hours is a standard and sensible approach.
- NICU care afterwards, with intravenous nutrition until bowel function returns.
- Malrotation found without volvulus is usually corrected electively with a Ladd procedure, which can be laparoscopic in suitable children.
Does My Child Need Surgery?
Not every child with Malrotation & Volvulus needs an operation. These are the situations in which surgery is advised — and the decision is always made after examining your child, never from a description alone.
Immediately, when volvulus is suspected in a baby with bile-stained vomiting — this is measured in hours, not days
Electively, when malrotation is found without twisting, to prevent a future volvulus
In an older child with recurrent symptoms and confirmed malrotation
There is no medical treatment for a twisted bowel
What Happens Over Time
Excellent when a volvulus is untwisted before the bowel is damaged — children recover fully and lead normal lives. This is the condition where hours genuinely change the outcome, because extensive bowel loss has lifelong nutritional consequences. Malrotation corrected electively, before any twisting, does very well.
This describes what usually happens, not what will happen to your child. The surgeon will give you a specific picture after examining them.
Can It Be Prevented?
The malrotation itself cannot be prevented. A volvulus and its consequences very often can be, by treating bile-stained vomiting in a baby as an emergency every single time.
From First Visit to Going Home
What happens, in order, so that nothing on the day comes as a surprise.
Consultation
Dr. Pratheep Samraj examines your child and goes through the history, earlier reports and any treatment already given.
Investigation
Only the tests that change the decision are asked for — commonly an ultrasound, blood tests, and occasionally an X-ray or a scopy.
Explanation
You are told what the condition is, whether it needs surgery, what happens if you wait, and what the operation involves.
Treatment
If surgery is appropriate it is planned with paediatric anaesthetic cover, with ICU and NICU support available in the hospital.
Follow-up
You go home with written instructions and a review date, and you can reach the hospital by phone or WhatsApp in between.
Hospital stay
A week or more, and considerably longer if bowel had to be removed or the baby needed prolonged intravenous nutrition.
Recovery at home
Depends heavily on how much bowel was salvaged. Feeds are reintroduced gradually and tolerance is built up over days to weeks.
Follow-up
Growth, nutrition and bowel function, with close attention where a significant length of bowel was lost.
Please bring with you: all previous scan reports, blood test reports, discharge summaries, records of any earlier operation, current medicines, and your child’s immunisation card. Photographs on your phone of a swelling that comes and goes are genuinely useful.
Please note: this page is general information about Malrotation & Volvulus, not advice about your child. Timing, suitability for surgery and the expected result differ from child to child and are decided only after clinical evaluation.
Questions Parents Ask
If your question is not here, send it on WhatsApp — you will get an answer from the hospital team.
Dr. Pratheep Samraj
Consultant Paediatric & Neonatal Surgeon · Palliyadi, Kanyakumari
Super-specialist surgical care for newborns, infants and children, with expertise in paediatric urology, congenital anomalies, gastro-intestinal surgery and minimally invasive surgery.
Related Conditions
Volvulus can cost a child their bowel in a matter of hours.
Green vomiting in a baby is malrotation until proved otherwise. Of everything on this site, this is the one that should never wait for an appointment.
Consultation 10:00 AM - 1:00 PM & 4:00 PM - 8:00 PM · 24-hour laboratory & pharmacy
In an emergency — green vomiting in a baby, a groin swelling that will not go back, severe tummy pain, or a newborn not passing urine or meconium — come straight to the hospital or to your nearest emergency department. Do not wait for a reply to a message.