Reflux & Vomiting in Children
When bringing up feeds is normal — and when it is not.
What is Reflux & Vomiting in Children?
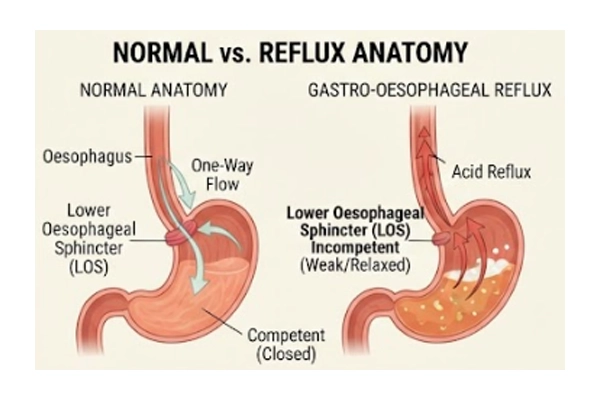
Reflux means stomach contents coming back up into the food pipe. In babies it is extremely common and usually harmless — the valve at the top of the stomach is immature, and most babies grow out of it by about a year.
Simple reflux in a baby who is feeding well and gaining weight needs reassurance and small practical measures, not investigation.
It becomes significant — gastro-oesophageal reflux disease — when it causes poor weight gain, pain, feed refusal, blood in the vomit, or recurrent chest infections from aspiration.
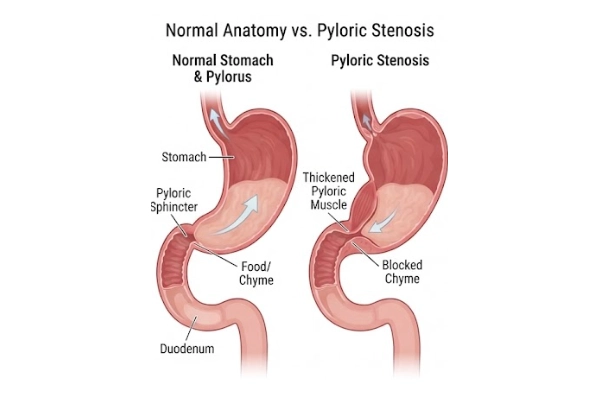
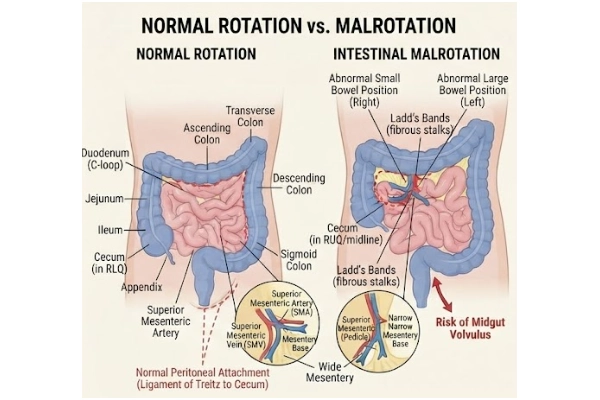
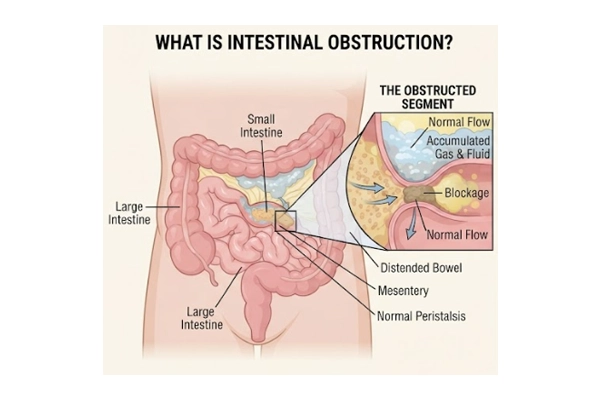
The critical job at the consultation is to separate harmless reflux from vomiting that signals something else: pyloric stenosis, malrotation, obstruction, raised pressure in the head, or infection. The colour and pattern of the vomit and the child’s weight chart do most of that work.
In your language
Reflux & Vomiting in Children
When bringing up feeds is normal — and when it is not.
Reflux means stomach contents coming back up into the food pipe. In babies it is extremely common and usually harmless — the valve at the top of the stomach is immature, and most babies grow out of it by about a year.
குழந்தைகளில் அமில ரிஃப்ளக்ஸ் & வாந்தி
குழந்தைகள் பால் குடித்தபின் சிறிதளவு திரும்ப எடுப்பது (posseting) மிகவும் சாதாரணம் — குழந்தை நன்றாக எடை கூடிக்கொண்டிருந்தால் கவலை வேண்டாம். பெரும்பாலான குழந்தைகளுக்கு ஒரு வயதிற்குள் இது தானாகவே சரியாகும். ஆனால் இந்த அறிகுறிகள் இருந்தால் உடனே பரிசோதிக்க வேண்டும்: பச்சை நிற வாந்தி, பீய்ச்சி அடிக்கும் வாந்தி, எடை கூடாமை, ரத்தம் கலந்த வாந்தி, வயிறு உப்புதல், அடிக்கடி நெஞ்சு தொற்று. அனைத்து வாந்தியும் ரிஃப்ளக்ஸ் அல்ல — வாந்தியின் நிறமும் குழந்தையின் எடையும்தான் முக்கியம்.
കുട്ടികളിലെ റിഫ്ലക്സും ഛർദ്ദിയും
കുഞ്ഞുങ്ങൾ പാൽ കുടിച്ചശേഷം അല്പം തിരികെ വരുന്നത് വളരെ സാധാരണമാണ് — കുഞ്ഞ് നന്നായി തൂക്കം കൂടുന്നുണ്ടെങ്കിൽ പേടിക്കേണ്ട. മിക്ക കുഞ്ഞുങ്ങളിലും ഒരു വയസ്സാകുമ്പോഴേക്കും ഇത് സ്വയം മാറും. എന്നാൽ ഈ ലക്ഷണങ്ങളുണ്ടെങ്കിൽ ഉടൻ പരിശോധിക്കണം: പച്ച ഛർദ്ദി, ശക്തിയായി ചീറ്റുന്ന ഛർദ്ദി, തൂക്കം കൂടാതിരിക്കൽ, രക്തം കലർന്ന ഛർദ്ദി, വയറു വീർക്കൽ, ആവർത്തിച്ചുള്ള നെഞ്ചിലെ അണുബാധ. എല്ലാ ഛർദ്ദിയും റിഫ്ലക്സ് അല്ല.
What Parents Notice
Not every child shows every sign. If something on this list matches your child, it is worth an examination rather than a guess.
- Effortless bringing up of small amounts of milk after feeds in a thriving baby — usually normal
- Arching, crying and irritability during or after feeds
- Refusing feeds, or feeding briefly and pulling away
- Poor weight gain or weight loss
- Recurrent cough, wheeze or chest infections
- Blood in the vomit, or coffee-ground vomit
- Danger signs that mean this is not simple reflux: green or yellow-green vomiting, forceful projectile vomiting, a swollen tummy, blood in the stool, fever with lethargy, a bulging soft spot, or vomiting starting suddenly after 6 months of age
How It Is Confirmed
- History and examination with careful attention to the growth chart — often enough to make the diagnosis in a thriving baby
- Ultrasound of the abdomen where pyloric stenosis or another structural cause is suspected
- Upper GI contrast study where malrotation must be excluded — particularly with bile-stained vomiting
- Upper gastro-intestinal endoscopy in selected children with significant symptoms, bleeding or failure to respond
- Blood and urine tests where infection or a metabolic cause is possible
How It Is Treated
- Simple measures first: smaller more frequent feeds, effective winding, keeping the baby upright after feeds, and checking feeding technique and volumes.
- A trial of a thickened or hypoallergenic feed where cow’s milk protein allergy is suspected.
- Acid-suppressing medication for a limited period in children with genuine reflux disease — not routinely for every baby who posits.
- Nutritional support where growth is affected.
- Anti-reflux surgery (fundoplication) is reserved for a small minority: children with severe reflux causing aspiration or failure to thrive despite full medical treatment, and children with neurological impairment in whom reflux is severe.
- Any structural cause found — pyloric stenosis, malrotation, hiatus hernia — is treated on its own merits.
Does My Child Need Surgery?
Not every child with Reflux & Vomiting in Children needs an operation. These are the situations in which surgery is advised — and the decision is always made after examining your child, never from a description alone.
Reflux causes recurrent aspiration or life-threatening episodes
Growth fails despite proper medical treatment and feeding support
There is a hiatus hernia or another anatomical cause
The child is neurologically impaired with severe reflux and needs feeding surgery
For the great majority of babies with reflux, surgery is not appropriate and time is the treatment
What Happens Over Time
Excellent for the ordinary reflux of infancy: the great majority of babies grow out of it by about a year as they mature and start solids. Reflux severe enough to affect growth or the lungs is less common and needs active treatment, occasionally including surgery.
This describes what usually happens, not what will happen to your child. The surgeon will give you a specific picture after examining them.
Can It Be Prevented?
Simple reflux cannot be prevented and does not need to be. Smaller more frequent feeds, effective winding and keeping the baby upright after feeds reduce how much it happens.
From First Visit to Going Home
What happens, in order, so that nothing on the day comes as a surprise.
Consultation
Dr. Pratheep Samraj examines your child and goes through the history, earlier reports and any treatment already given.
Investigation
Only the tests that change the decision are asked for — commonly an ultrasound, blood tests, and occasionally an X-ray or a scopy.
Explanation
You are told what the condition is, whether it needs surgery, what happens if you wait, and what the operation involves.
Treatment
If surgery is appropriate it is planned with paediatric anaesthetic cover, with ICU and NICU support available in the hospital.
Follow-up
You go home with written instructions and a review date, and you can reach the hospital by phone or WhatsApp in between.
Hospital stay
Medical management is outpatient. Fundoplication, where indicated, means several days in hospital.
Recovery at home
Most babies improve steadily over months as they mature and start solids. After fundoplication, feeds are built up gradually.
Follow-up
Weight and growth are the practical measures, with review to step treatment down once symptoms settle.
Please bring with you: all previous scan reports, blood test reports, discharge summaries, records of any earlier operation, current medicines, and your child’s immunisation card. Photographs on your phone of a swelling that comes and goes are genuinely useful.
Please note: this page is general information about Reflux & Vomiting in Children, not advice about your child. Timing, suitability for surgery and the expected result differ from child to child and are decided only after clinical evaluation.
Questions Parents Ask
If your question is not here, send it on WhatsApp — you will get an answer from the hospital team.
Dr. Pratheep Samraj
Consultant Paediatric & Neonatal Surgeon · Palliyadi, Kanyakumari
Super-specialist surgical care for newborns, infants and children, with expertise in paediatric urology, congenital anomalies, gastro-intestinal surgery and minimally invasive surgery.
Related Conditions
Most bringing up of feeds is normal. A few things make it not normal.
Poor weight gain, blood, arching in pain or breathing trouble change the picture entirely. If your baby is thriving you may need reassurance rather than a medicine — come and be told which.
Consultation 10:00 AM - 1:00 PM & 4:00 PM - 8:00 PM · 24-hour laboratory & pharmacy
In an emergency — green vomiting in a baby, a groin swelling that will not go back, severe tummy pain, or a newborn not passing urine or meconium — come straight to the hospital or to your nearest emergency department. Do not wait for a reply to a message.